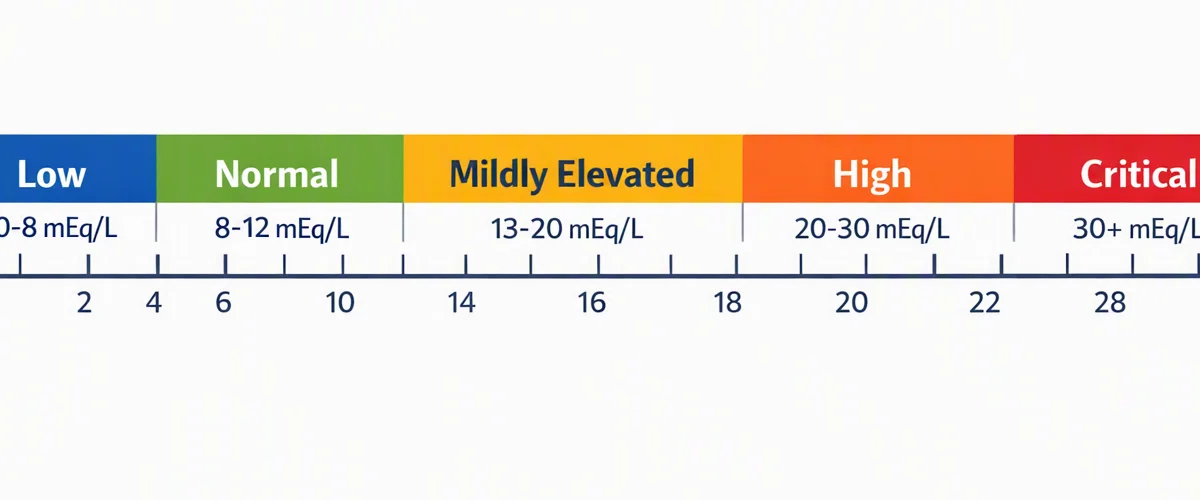
What the anion gap measures
The anion gap is a computed value that aids clinicians in understanding acid-base balance and the overall pattern of electrolytes in the blood. It is usually determined from the relationship between sodium, chloride, and bicarbonate, with the result reflecting what is left unmeasured in routine blood chemistry. In simple terms, the anion gap gives clues about whether there may be extra acids in the body that are not obvious on a standard lab result.
Because the body maintains a tightly regulated buffer system, changes in the anion gap can signal a metabolic disorder before other values look clearly abnormal. A high anion gap often indicates acid accumulation from an underlying cause such as lactic acid, ketones, or certain toxins. That is why lab interpretation of this number matters: it can reveal a type of hidden acidosis that may not yet have changed the bicarbonate much.
Most routine reports include a basic metabolic panel, which provides the ingredients used for anion gap calculation. In some settings, an electrolyte panel may provide similar information. The values for sodium and chloride are central to the calculation, and the bicarbonate value, sometimes reported as serum CO2, helps estimate how much base is available in the blood. When the gap is high, clinicians think carefully about the clinical significance rather than focusing on one number alone.
How to work with an Anion Gap Calculator
An Anion Gap Calculator is a basic tool that helps calculate the gap from common lab numbers. In most cases, it uses sodium, chloride, and bicarbonate from a blood test. Some calculators also allow input for albumin, because low albumin can leave the result appear lower than it truly is. This is where careful medical review becomes important: the calculator is only as useful as the numbers entered and the context in which they are interpreted.
When using an Anion Gap Calculator, start with the basic metabolic panel or electrolyte panel. Check whether the bicarbonate is listed as bicarbonate or serum CO2, since many labs use serum CO2 as a surrogate for bicarbonate. Then verify the sodium and chloride values. If albumin is low, the corrected anion gap may be more precise than the unadjusted result.
This is a useful example of how lab interpretation and diagnostic workup work together. The calculator can reveal a pattern, but it cannot tell you the underlying cause. A high gap with normal bicarbonate may still indicate an evolving problem, especially if symptoms or other blood chemistry findings suggest acid-base status changes. The calculator is best used as a starting point for evaluation steps, not a final diagnosis.
For best results, remember these practical points:
- Use current serum values rather than old results. Verify whether bicarbonate is reported as bicarbonate or serum CO2. Consider albumin before accepting a “normal” gap at face value. Evaluate the result alongside symptoms and the rest of the blood chemistry.
What normal bicarbonate with increased anion gap can suggest
A normal bicarbonate with a increased anion gap often means there is a problem causing extra acid to collect, but the bicarbonate has not yet decreased much or is being maintained by a compensatory response. This finding can appear in early acid-base disturbance, before the lab changes become more obvious. It can also happen if one disorder is counteracted by another, creating a picture that looks less severe on the surface than it really is.
One major concern is high anion gap metabolic acidosis. This term describes acidosis caused by unmeasured acids, such as those seen in acid buildup from lactate or acid buildup from ketones. In these conditions, bicarbonate may still be in the reference range if the problem is early, if there is partial compensation, or if another process is pushing bicarbonate upward at the same time.
Lactic acidosis can develop when tissues are not getting enough oxygen or when the body is under severe stress. Ketone acidosis can occur when ketones accumulate, often during fasting, illness, or diabetes-related insulin deficiency. Toxic alcohols are another important cause of a high gap. These substances create acids after being metabolized, and the bicarbonate may lag behind early in the course.
So, normal bicarbonate does not necessarily mean the acid-base picture is normal. It may indicate:
- early acid accumulation limited compensation a combined acid-base disorder a raised anion gap that has not yet reduced bicarbonate
The key is to interpret the result in the broader medical meaning of the patient’s presentation, not as an isolated number.
Frequent causes underlying this laboratory pattern
A number of conditions can lead to a raised anion gap even when bicarbonate seems normal. One frequent cause is renal failure, where the kidneys cannot remove acids efficiently. As acids accumulate, the gap goes up. Depending on timing and compensatory effects, bicarbonate may still seem acceptable on an early or partial test.
Diabetic ketoacidosis is another important cause. In this condition, the body produces large amounts of ketones, which raise the anion gap. Although bicarbonate is often low in classic cases, it may be near normal early on or affected by another acid-base process. That is why serum ketones and glucose are often ordered when the pattern is suspicious.
Sepsis can also lead to lactic acidosis because poor tissue perfusion and metabolic stress increase lactate production. In some patients, this creates a high anion gap before bicarbonate drops significantly. The lab pattern can be subtle, especially if other factors are influencing the blood chemistry.
Salicylate poisoning is a classic mixed acid-base picture. Salicylates can cause a combination of respiratory and metabolic effects, which means bicarbonate may not behave as expected. This is one reason clinicians pay close attention to the full acid-base status, rather than relying on a single lab value.
Other important toxins include toxic alcohols such as methanol and ethylene glycol. These substances can create a dangerous high gap metabolic pattern, sometimes before all routine values become abnormal. A careful symptom assessment and timely medical review are essential when exposure is possible.
Reasons why bicarbonate may still also look normal
Several reasons exist bicarbonate may remain normal despite a high anion gap. One is compensation. The body continuously adjusts breathing and kidney function to preserve acid-base balance. If a problem is developing slowly, the system may temporarily keep bicarbonate in the normal range even while acids are accumulating.
Another reason is a mixed acid-base disorder. In this situation, two processes are happening at the same time. For example, a person may have a high anion gap metabolic process plus respiratory alkalosis, which can push values in opposite directions. The net effect may be a bicarbonate level that looks deceptively normal, even though the patient has significant acid-base disturbance.
Early metabolic acidosis is also a frequent explanation. In early stages, the extra acid may be reflected first in the anion gap, while bicarbonate has not yet dropped enough to leave the reference range. This is one reason a “normal” bicarbonate should not end the evaluation if symptoms, history, or other labs suggest a problem.
In practical terms, a normal bicarbonate does not always mean the buffer system is stable. It may mean the body is still maintaining a temporary balance. That is why clinicians combine the lab pattern with the rest of the evaluation, including the timing of symptoms, possible exposures, and the full diagnostic workup.
How albumin affects the anion gap
Albumin is one of the primary unmeasured ions that changes the anion gap. When albumin is decreased, the measured anion gap can seem falsely normal or only somewhat elevated. This is called hypoalbuminemia, and it can lead to confusing laboratory interpretation if the albumin level is not considered.
To account for this, clinicians may determine a corrected anion gap. The correction helps show what the gap would appear if serum albumin were normal. This can detect hidden acid-base abnormalities that would otherwise be missed. In other words, the corrected value may present a more informative picture of acid accumulation than the raw number alone.
This adjustment matters because albumin is a key part of blood chemistry and a significant part of the anion gap interpretation process. A patient with low albumin can have a dangerous acid-base problem even if the standard gap seems unimpressive. That is why albumin should be part of the medical review whenever the gap and bicarbonate do not seem to fit the clinical picture.
When the albumin level is low, think about:
- reduced baseline anion gap from hypoalbuminemia importance for corrected anion gap calculation possible hidden acidosis greater importance of the full clinical context
When a high anion gap is urgent
A high anion gap may be urgent when it appears with emergency symptoms like confusion, severe weakness, rapid breathing, vomiting, chest pain, or decreased responsiveness. These signs can indicate serious acid-base problems, toxin exposure, poor perfusion, or severe infection. Even if bicarbonate is still normal, the combination may indicate a rapidly evolving condition that needs prompt attention.
In emergency settings, clinicians often order a blood gas to assess acid-base status more precisely. A blood gas can help determine whether the body is compensating and whether the problem is metabolic, respiratory, or mixed. It gives more detail than the basic metabolic panel alone.
Further urgent testing may involve lactate and ketones. Elevated lactate can support lactic acidosis, while ketones can point toward ketoacidosis or diabetic ketoacidosis. When there is concern about toxic alcohols or salicylates, specific toxicology testing may be needed quickly.
When the high anion gap is accompanied by infection signs, kidney issues, altered mental status, or known ingestion risk, it deserves immediate medical evaluation. The main concern is not only the value itself, but also the pattern, symptoms, and possible underlying cause.
Which additional tests may be ordered
When the lab pattern suggests a high anion gap but bicarbonate is still normal, the usual next step is a focused diagnostic workup. An early test may be an arterial blood gas, which provides a clearer picture of pH, carbon dioxide, and bicarbonate status. This helps clinicians confirm whether the patient albumin corrected anion gap in hypoalbuminemia truly has acid-base disturbance and whether a compensatory response is present.
Repeat electrolytes is also common. As lab values may shift rapidly, repeating the electrolyte panel or basic metabolic panel may show whether the gap is increasing, unchanged, or improving. Trends are often more helpful than a single chemistry result.
Additional useful tests include glucose and creatinine. Glucose helps identify diabetes-related causes such as diabetic ketoacidosis, while creatinine helps evaluate renal failure or decreased kidney clearance of acids. If symptoms or history point to a metabolic issue, these tests are often included in the initial evaluation.
Depending on the context, clinicians may also check:
- lactate to assess for lactic acidosis ketones for ketoacidosis toxicity testing for salicylates or toxic alcohols extra serum values to better define the acid-base status
The aim is to find the underlying cause before the condition worsens. A normal bicarbonate should not stop the workup if the overall pattern suggests hidden acidosis or another serious process.
Frequently asked questions
What does a high anion gap with normal bicarbonate mean?
It generally means there may be extra acid in the body, but bicarbonate has not decreased yet or is staying normal because of compensation or a mixed acid-base disorder. It may be an early sign of high anion gap metabolic acidosis, including lactic acidosis, ketoacidosis, renal failure, or toxin exposure.
Can someone have metabolic acidosis if bicarbonate is normal?
Yes, it can. Mild metabolic acidosis, compensation, or a mixed acid-base disorder can keep bicarbonate in the normal range for a while. That is why anion gap interpretation is important even when the bicarbonate looks normal.
Which are the most common causes of a high anion gap?
Common causes include lactic acidosis, ketoacidosis, diabetic ketoacidosis, renal failure, salicylate poisoning, and toxic alcohols. Sepsis and other serious illnesses can also contribute by increasing acid production or reducing acid clearance.
Does a normal bicarbonate rule out an acid-base problem?
No. A normal bicarbonate does not rule out acid-base disorders. It may hide early disease, compensation, or a mixed acid-base disorder. Clinical significance depends on the full picture, not one lab value alone.
When should a high anion gap be considered urgent?
It should be considered urgent when it occurs with emergency symptoms, altered mental status, rapid breathing, severe illness, or known toxin exposure. A blood gas, lactate, ketones, repeat electrolytes, and other tests may be needed right away to identify the cause.