What the Anion Gap Measures
The anion gap is a derived value that helps clinicians evaluate electrolytes and interpret acid-base balance. It is commonly used as part of the workup for metabolic acidosis, notably when the cause is not immediately obvious. An Anion Gap Calculator is merely a tool that performs the calculation from the key laboratory values, but the result is only as useful as the data entered and the clinical context around it.
In clinical terms, the anion gap estimates the difference between the positively charged and negatively charged particles measured in the blood. Because routine chemistry panels do not measure every ion, the result can suggest whether there are unmeasured anions driving an acid-base disorder. That makes the anion gap a useful piece of laboratory values interpretation, especially when assessing a potential metabolic derangement.
The anion gap is not a standalone diagnosis. It is a screening and interpretive clue that must be interpreted alongside symptoms, physical findings, and other tests. When used correctly, it helps narrow the causes of altered acid-base status and points toward conditions that may require urgent attention.
Panels Needed for Anion Gap Calculation
The key labs used for anion gap calculation are sodium, chloride, and bicarbonate. They are typically reported on a basic metabolic panel and often frequently appear on a comprehensive metabolic panel or electrolyte panel. Most Anion Gap Calculator tools use these three values in the typical formula.
The usual formula is:
Anion gap = sodium - (chloride + bicarbonate)
In many lab reports, bicarbonate may be listed as serum CO2. In routine chemistry testing, serum CO2 is used as a common surrogate for bicarbonate, so the reported number is typically the value entered into an anion gap calculator. That is one reason why understanding the exact label on the panel matters.
A basic metabolic panel is often the quickest way to obtain the needed values. A comprehensive metabolic panel includes the same electrolytes plus extra serum chemistry markers, so it can also support the calculation. If the patient already has either panel, the anion gap can usually be derived without ordering extra testing.
For reliable calculation, the labs should come from the same sample or from closely timed sampling. Mixing values from different draws can create uncertainty in interpretation, especially if treatment has already started or if the patient’s status is changing rapidly.
How an Anion Gap Calculator Uses the Lab Values
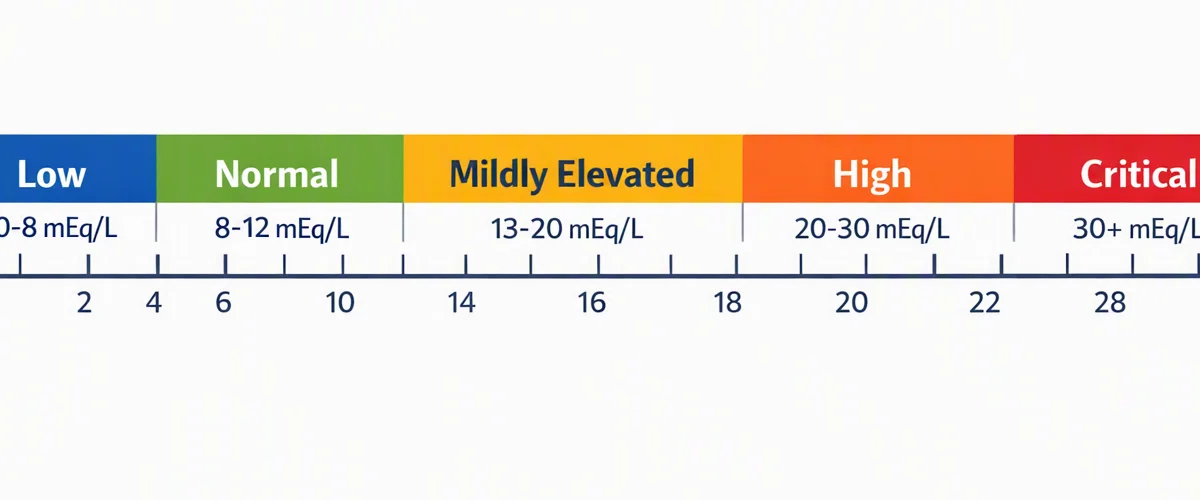
An anion gap calculator calculates the anion gap formula directly to the reported laboratory values. The calculation itself is straightforward, but the meaning of the result depends on the normal range used by the laboratory and on the patient’s clinical context. Different testing systems and report formats may produce slightly different reference intervals, so the local reference range matters.
Most calculators use sodium, chloride, and bicarbonate as the primary inputs. Some also allow additional correction for albumin, because albumin is a major unmeasured anion in blood and can substantially alter the result. If albumin is not included, the displayed result is the uncorrected anion gap.
The calculation works as a quick estimate of the balance between measured cations and measured anions. If chloride and bicarbonate are relatively high compared with sodium, the anion gap may be low or normal. If the difference is larger than expected, the result is elevated, which can suggest excess unmeasured anions.
Many clinicians use the anion gap as a initial interpretation tool rather than a final answer. It helps determine whether acidosis is likely due to a buildup of acids or due to a loss of bicarbonate with compensatory changes in chloride. In that sense, it is a practical part of bedside and laboratory-based calculation.
How Albumin Can Affect the Result
Albumin is among the key factors that can alter the anion gap. Because albumin has a negative charge, lower albumin levels can make the measured anion gap appear lower than expected. This is especially important in hypoalbuminemia, where the uncorrected value may underestimate the true degree of acid retention.
When albumin is reduced, clinicians may apply a corrected anion gap to better reflect the patient’s true acid-base condition. This adjustment helps consider the loss of negatively charged serum proteins. Without this step, a patient with significant metabolic acidosis could be seen as having a misleadingly normal result.
Not every situation requires correction, but it becomes more necessary when the patient has chronic illness, inflammation, malnutrition, liver disease, or fluid overload—situations in which albumin may be abnormal. If albumin is not available, the result can still be used, but the interpretation should be careful.
When using an Anion Gap Calculator, it is helpful to ask whether the tool reports a corrected or uncorrected result. If albumin is entered, the calculator may apply a correction formula that estimates the effect of hypoalbuminemia on the apparent gap. That can improve clinical accuracy, especially when evaluating acid-base status in complex cases.
When Additional Labs May Be Added
Even though sodium, chloride, and bicarbonate are the core tests, additional studies are often added to determine the cause of an abnormal gap. An arterial blood gas or another blood gas measurement may be obtained to assess pH, pCO2, and the overall acid-base disorder. This is especially helpful when the bicarbonate value alone does not fully explain the clinical picture.
Lactate is commonly checked when lactic acid accumulation is suspected. Elevated lactate can lead to a high anion gap metabolic acidosis, and it is an important clue in patients with sepsis, poor perfusion, hypoxia, or other states of tissue stress. In the right setting, checking lactate is key for a more complete diagnostic assessment.
Ketones are another common add-on test, particularly when diabetic ketoacidosis is a concern. Ketone production can raise an elevated anion gap and is a classic cause of metabolic acidosis. If glucose is high or symptoms fit, ketone testing can determine whether ketoacidosis is contributing to the laboratory pattern.
Renal function testing is also often ordered. Creatinine, blood urea nitrogen, and related markers help determine whether kidney impairment is reducing acid excretion. A decline in renal function can be associated with accumulation of acids and a rising gap, so these values support the overall interpretation.
Based on the scenario, clinicians may also order a broader electrolyte panel or repeat the chemistry tests to confirm a surprising result. Rechecking can help rule out sampling error, specimen handling issues, or a transient change that is already resolving.
Reading the Difference Between a High and Normal Anion Gap
A elevated anion gap metabolic acidosis implies that more acids are circulating in the blood or that unmeasured acids have accumulated. This often indicates excess unmeasured acids such as lactate, ketoacids, or toxins. The term is explanatory rather than diagnostic, so the clinical interpretation must identify the underlying cause.
A non-elevated anion gap metabolic acidosis can still be clinically significant. In this pattern, bicarbonate is low, but the gap remains within the expected normal range because chloride rises to offset the loss. This is often called hyperchloremic metabolic acidosis. The result does not exclude acidosis; it simply indicates a different mechanism.
Assessing the result requires attention to the full clinical context. A patient with severe symptoms, abnormal pH on a blood gas, or concerning laboratory trends may need immediate treatment regardless of whether the gap is high, normal, or borderline. The anion gap is best used as part of a broader medical interpretation rather than in isolation.
One useful way to think about the result is this: a high gap often reflects hidden acid burden, while a normal gap suggests either no major accumulation of unmeasured anions or a separate process that lowers bicarbonate without widening the gap. Either way, the result is a pointer, not the final answer.
Typical Causes That Affect the Anion Gap
Several conditions can change the anion gap, but certain causes are especially important because they are frequent and clinically time-sensitive. Lactic acidosis is a key cause of elevated gap and may occur with systemic infection, shock, hypoxia, seizures, or medication effects. Because lactate reflects impaired oxygen use or transport, it often requires prompt evaluation.
Diabetic ketoacidosis is another classic cause. In this condition, ketone acids increase when the body has too little of sufficient insulin or cannot use glucose well. Ketones decrease bicarbonate and elevate the anion gap, which is why both serum chemistry and ketone testing are so useful together.
Kidney failure can also elevate the gap because the kidneys cannot adequately clear acid load or maintain normal balance of electrolytes and bicarbonate. As renal function declines, acids collect and the laboratory pattern may become more obvious.
Toxic alcohols are an important consideration in patients with unexplained high-gap acidosis. These exposures can generate organic acids and lead to a dangerous metabolic profile. When history, symptoms, or lab findings suggest possible ingestion, prompt toxicology evaluation is warranted.
Other causes may include starvation, severe illness, certain medications, and less common metabolic disorders. interpret low anion gap The anion gap helps organize the differential diagnosis, but it should never replace targeted history-taking, examination, and follow-up testing.
How to Operate an Anion Gap Calculator Properly
To use an Anion Gap Calculator properly, begin with entering the correct lab values from the same specimen whenever possible. Confirm the units and make sure the bicarbonate field corresponds to either bicarbonate or serum CO2, depending on how the calculator is designed. An inconsistency here can lead to a misleading result.
Next, review the reference range used by the calculator or the laboratory report. Normal values can differ slightly by method, analyzer, and institution. A result that seems mildly elevated in one setting may fall within the local normal range in another. This is why the lab-specific interval matters so much in interpretation.
Focus on unit consistency. Sodium, chloride, and bicarbonate should be in the expected format and not mixed with values from a different panel or unit system. Proper input helps ensure that the formula gives a reliable result.
It also helps to know whether the source data came from a basic metabolic panel, a comprehensive metabolic panel, or a standalone electrolyte panel. All can provide the needed values, but each may have different additional markers that support clinical assessment. For example, a CMP can help pair the anion gap with liver-related or protein-related findings, while a BMP is often focused more tightly on kidney and electrolyte assessment.
Lastly, interpret the result in the full clinical context. The calculator can show whether the gap is increased, decreased, or within range, but the meaning depends on symptoms, trends, and associated tests. A good result from an Anion Gap Calculator is one that helps direct the next diagnostic step, not one that stands alone.
Common Questions
What labs are required to calculate the anion gap?
The required labs are sodium, chloride, and bicarbonate. In many reports, bicarbonate appears as serum CO2. These values are usually anion gap in chronic kidney disease taken from a basic metabolic panel, a comprehensive metabolic panel, or an electrolyte panel.
Does an anion gap calculator need albumin?
Not in every case, but albumin is especially useful when present. Reduced albumin can lower the measured gap, so a calculator that includes albumin can calculate a corrected anion gap. That is especially useful in hypoalbuminemia.
Can the anion gap be calculated from a CMP or BMP?
Absolutely. A basic metabolic panel and a comprehensive metabolic panel typically contain the necessary values for anion gap calculation. Both usually include sodium, chloride, and bicarbonate or serum CO2, which are sufficient for the standard formula.
What does a high anion gap mean?
A high anion gap usually suggests a buildup of unmeasured anions and is often associated with high anion gap metabolic acidosis. Common causes include lactic acid accumulation, ketones, diabetic ketoacidosis, kidney failure, and toxic alcohols.
Why might an anion gap be normal even when acidosis is present?
Such a pattern can occur in normal anion gap metabolic acidosis, where bicarbonate is lost but chloride rises enough to keep the gap in the reference range. In that situation, acidosis is still present, but the mechanism is different, so the result must be interpreted with medical interpretation and often a blood gas.