What exactly is the anion gap?
The anion gap is a computed value that aids clinicians analyze an electrolytes panel and evaluate acid-base balance. It contrasts the main reported positive ions and negative ions in blood, especially sodium, chloride, and bicarbonate. Because not all ions are measured directly, the result gives a useful diagnostic clue about whether there may be excess acids or other unmeasured anions in the bloodstream.
At its core, the anion gap reflects the difference between measured cations and measured anions. In routine practice, it is most often used as part of a broader electrolyte panel review when evaluating metabolic acidosis or other forms of systemic acidosis. A normal value points to one pattern of clinical interpretation, while an elevated value suggests another. The number itself does not confirm the diagnosis, but it supports narrow the differential diagnosis.
Think of the anion gap as a view of the chemical balance in the blood. If bicarbonate falls, something else must often be taking its place. That “something else” may be acids that do not show up on a standard panel. The resulting gap calculation can assist a workup, but it must always be read alongside the patient’s symptoms, history, and other laboratory values.
How an anion gap calculator operates
An Anion Gap Calculator automates the standard formula used to calculate the gap from common blood chemistry results. The classic calculation is:
Anion gap = sodium − (chloride + bicarbonate)
Some labs and clinicians use alternative formulas that include potassium, but the sodium-based version is the most common. The calculation uses the measured sodium as the main cation and subtracts the sum of chloride and bicarbonate, which are the main measured anions. The result is a quick way to estimate whether there are additional charged particles in the blood that are not being directly counted.
Why does this matter? Because a drop in bicarbonate often indicates an acid-base problem, but the cause of that drop can be different. A calculator makes the process quick and reduces manual errors, especially when reviewing several laboratory values at once. It also helps clinicians quickly compare the result with the expected reference range and decide whether the pattern suggests high or normal gap metabolic derangement.
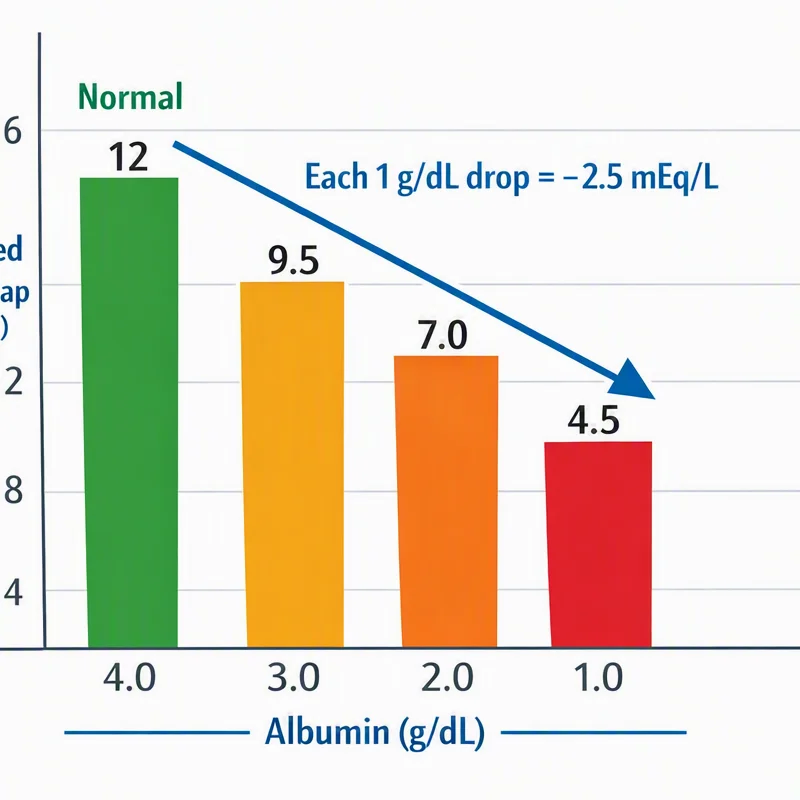
Albumin also matters. Since albumin is a major negatively charged protein in the bloodstream, low albumin can lower the calculated gap and make the result look less concerning than it really is. That is why many clinicians use an albumin-corrected anion gap for more accurate result interpretation. In other words, the calculator gives a useful estimate, but not the final answer.
Can the anion gap help diagnose acidosis causes?
Certainly. The anion gap is one of the most useful tools for sorting out the cause of metabolic acidosis. It does not confirm a disease by itself, but it serves separate acidosis into two major patterns: high anion gap acidosis and normal anion gap acidosis. That separation often directs the rest of the workup.
A high gap usually means acids have built up in the blood, increasing unmeasured anions. A normal gap usually means bicarbonate has been removed and replaced by chloride, which keeps the gap from rising. This is why the pattern counts so much for clinical interpretation. The same low bicarbonate level can stem from very different processes.
A blood gas is often used together with the anion gap to verify whether acidemia is present and whether compensation is appropriate. A blood gas helps show pH, carbon dioxide, and bicarbonate status, while the gap provides a clue about the underlying cause. Together, they strengthen the acid-base evaluation.
In practical terms, the anion gap helps answer three questions:
- Is there metabolic acidosis? If yes, is it high gap or normal gap? What extra testing should be done?
That makes it a strong diagnostic clue, but not a standalone diagnosis. The most accurate approach integrates the gap calculation, the blood gas, and the patient’s story.
High anion gap acidosis: common causes
High anion gap acidotic state develops when acids collect and deplete bicarbonate. The usual causes are often listed as a short set, but the practical differential diagnosis can be more extensive. Major causes include lactic acidosis, ketoacidosis, kidney failure, and toxins.
Lactic acidosis occurs when tissues produce or clear lactate abnormally. This can happen with low oxygen supply, shock, severe infection, seizures, or other states of stress. The excess lactate acts as an unmeasured anion, raising the gap. In many cases, a serum serum lactate level is one of the most important next tests.
Ketoacidosis arises when fat breakdown intensifies and ketone production rises. It may be seen in uncontrolled diabetes, prolonged fasting, alcohol use, or other metabolic stress states. Here, checking ketones is essential because they often account for the acid load.
Kidney failure can also cause high gap acidosis because the kidneys cannot clear acid properly. As renal function worsens, acids accumulate and bicarbonate drops. This is a typical example of acid-base imbalance that may look subtle at first but becomes more obvious with worsening clinical interpretation of the chemistry profile.
Toxins are another key category. Some ingestions create unusual acids or disrupt normal metabolism, leading to marked gap elevation. Because some toxic causes can be time-sensitive, a careful history is crucial, and toxic exposures should remain part of the differential diagnosis whenever the pattern does not fit the usual explanations.
High-gap patterns often suggest the presence of extra acid, not just bicarbonate loss. That is why the anion gap is so important: it helps identify a problem that may not be obvious from the electrolyte panel alone.
Normal anion gap acidosis: frequent causes
A non-anion-gap acidosis, also called chloride-rich acidosis, usually means bicarbonate has been depleted and replaced by chloride. The gap stays “normal” because the fall in bicarbonate is matched by a rise in chloride, producing a chloride change that keeps the calculation stable.
One common cause is diarrhea. When the gastrointestinal tract loses bicarbonate-rich fluid, the body becomes more acidic. This is often described as gastrointestinal bicarbonate loss. In these cases, chloride often rises as the body attempts to maintain electrical neutrality, which is why the acidosis does not necessarily produce a high gap.
Another important cause is renal tubular acidosis. In this condition, the kidneys do not handle acid and bicarbonate normally, so bicarbonate is lost or acid is retained despite a preserved or near-preserved glomerular filtration rate. Depending on the type, potassium abnormalities may also be present, making a careful workup important.
Hyperchloremic acidosis is a useful label because it describes the pattern rather than the cause. That pattern points clinicians toward GI losses, renal tubular problems, or other states where bicarbonate is depleted but unmeasured anions are not the main issue. This is a very different diagnostic pathway from high-gap acidosis.
So, if the gap is normal but the patient has low bicarbonate and acidemia, acidosis is still possible. The key is not to stop at the gap value alone. Instead, interpret it in the context of the blood gas, chloride level, and the overall metabolic picture.
Interpreting anion gap with correction for albumin
Albumin is a important negative-charge protein and has a major effect on the measured gap. When albumin is low, the anion gap can appear falsely normal or only mildly elevated even when a true acid-base problem exists. This is why hypoalbuminemia can conceal important changes.
An albumin-corrected anion gap adjusts the calculation to account for reduced protein binding and the loss of albumin’s negative charge contribution. This correction can reveal hidden acid-base disorders that would otherwise be missed. In patients with low albumin, especially those who are ill or hospitalized, correction enhances accuracy and promotes better result interpretation.
The logic is clear: less albumin means fewer measured negative charges in the baseline calculation. Without correction, the gap may miss the true burden of acids or unmeasured anions. With correction, the clinician gets a more realistic picture of the acid-base state.
Albumin adjustment is especially useful when the numbers do not fit the clinical picture. For example, a patient may have a concerning blood gas, low bicarbonate, and signs of systemic illness, but only a mildly abnormal gap. If albumin is low, the corrected value may show a how to correct AG for low albumin more significant abnormality.
In short, albumin correction enhances the quality of clinical interpretation. It does not substitute for judgment, but it helps avoid overlooking important metabolic acidosis.
Constraints of anion gap in diagnostic evaluation
Although the anion gap is extremely helpful, it has major limitations. One important issue is multiple acid-base disorders. A patient can have several process happening concurrently, such as high-gap metabolic acidosis plus alkalosis from vomiting, or a non-gap acidosis with another disorder occurring alongside it. In those situations, the gap may look less dramatic than expected.
Laboratory variation is another limitation. Different analyzers, methods, and reference ranges can produce minor shifts in the calculated value. A number that seems borderline abnormal in one lab may be considered normal in another. That is why the exact normal range should be interpreted according to the local laboratory.
The delta-delta gap can help identify mixed disorders by comparing the rise in anion gap with the fall in bicarbonate. If those changes do not match well, it may suggest another acid-base process is present. This is valuable, but it requires precise calculation and should still be integrated with the full clinical picture.
The biggest limitation is that the anion gap cannot diagnose the cause on its own. It is a clue, not a definitive diagnosis. Symptoms, medication history, kidney function, blood gas findings, and exposure history all matter. That is why the best results come from combining the gap with patient context and the broader metabolic assessment.
When you should order additional tests
Extra tests are often required whenever the gap is abnormal. or the patient seems very ill. If the concern is elevated gap acidosis, the recommended testing usually includes serum lactate, ketones, an arterial blood gas, and in some cases a toxicology screen. These tests help determine the cause and assess severity.
A serum lactate level is especially important when sepsis, shock, tissue hypoxia, or another form of poor perfusion is a concern. Elevated lactate supports lactic acidosis and may indicate urgent treatment needs.
Ketones help verify or exclude ketoacidosis. Depending on the scenario, urine ketones or serum beta-hydroxybutyrate may be more helpful than a basic screen. If diabetes, fasting, alcohol use, or starvation is suspected, ketone testing is a central part of the workup.
An arterial blood gas is valuable when the acid-base picture is unclear or when respiratory compensation needs to be measured accurately. It helps show the pH and carbon dioxide level, which are essential for complete acid-base evaluation.
A toxicology screen may be required when ingestion is possible or when the gap is high without an obvious reason. Some toxins can create severe metabolic acidosis, and early identification can change management.
Other tests may also be appropriate, such as kidney function studies, glucose, and targeted imaging, depending on the clinical picture. The key is that an abnormal gap should prompt purposeful next-step testing rather than be treated as a final diagnosis.
FAQ: Anion gap and acidosis
What does an anion gap show in acidosis?
The anion gap shows whether the low bicarbonate state is more suggestive of high anion gap or normal anion gap acidosis. It helps identify whether extra acids or bicarbonate loss is likely producing the problem. In other words, it is a useful tool for acid-base evaluation and differential diagnosis, not a diagnosis by itself.
Does a high anion gap always mean metabolic acidosis?
Not necessarily. A large gap strongly suggests metabolic acidosis, but mixed acid-base disorders can change the expected pattern. It needs interpretation with the blood gas, bicarbonate, and clinical context. The gap is an important clue, but it is not enough by itself to confirm the exact disorder.
Can a normal anion gap still indicate acidosis?
Absolutely. A normal gap can still appear in acidosis, especially in normal anion gap or hyperchloremic acidosis. Common examples include diarrhea, renal tubular acidosis, and other causes of GI bicarbonate loss. A low bicarbonate level with a normal gap still deserves a full acid-base workup.
Why do you correct the anion gap for albumin?
The gap is corrected because albumin adds negative charge to the calculation. In hypoalbuminemia, the raw number may miss the true abnormality. An albumin-corrected anion gap offers better accuracy and helps detect hidden acid-base disorders.
What tests should follow an abnormal anion gap?
Usual follow-up studies include serum lactate, ketones, an arterial blood gas, and a toxicology screen. The exact workup depends on the pattern, symptoms, and suspected cause. These tests help support the diagnosis, determine the driver of the acidosis, and shape treatment.