Why the anion gap Evaluates
The anion gap is a derived value used to assess electrolyte balance and support assessment of acid-base status. It allows clinicians interpret a laboratory result by calculating the difference between recorded cations and recorded anions in the blood. Because routine chemistry panels do not measure every charged particle, the anion gap gives insight into unmeasured anions that may be present during a metabolic disturbance.
An anion gap calculator is a helpful diagnostic tool for examining blood chemistry quickly. It is especially valuable when a patient has an electrolyte imbalance, since small shifts in sodium, chloride, bicarbonate, and related values can indicate an underlying acid-base disorder. In simple terms, the calculation helps show whether the blood has an excess of acids, an excess loss of base, or a pattern that matches electrolyte shift physiology.
The anion gap is not a anion gap in chronic kidney disease diagnosis by itself. It is part of broader acid-base analysis and should be interpreted alongside the full electrolyte panel, the serum bicarbonate level, and other clinical findings. Used well, it turns a basic chemistry snapshot into a more helpful picture of acid-base balance.
How the chloride shift Influences the Anion Gap
The chloride shift describes the shift of ions that serves to preserve electroneutrality in body fluids. In clinical interpretation, changes in chloride often occur in response to changes in bicarbonate. When bicarbonate falls, chloride may rise to maintain balance, which can keep the anion gap near normal even when an acid-base disorder is present.
This relationship is important because the chloride shift can mask or reveal a metabolic problem. For example, if bicarbonate is lost through the kidneys or gastrointestinal tract, the body may preserve or elevate chloride. The result is a pattern of normal anion gap acidosis, also called hyperchloremic acidosis. In this setting, the anion gap may not rise, even though the patient has clear metabolic acidosis.
By contrast, if acids accumulate and bicarbonate falls without a matching chloride increase, the anion gap rises. That pattern is more consistent with high anion gap acidosis. Understanding the chloride shift helps distinguish whether the chemistry reflects a gain of acids, a reduction in buffer, or a compensatory change in the buffer system.
For that reason, an anion gap calculator is especially valuable when reviewing chloride level changes. It helps relate the raw numbers to the underlying physiology and improves recognition of a true anion deficit versus a mere compensatory shift.
Anion Gap Formula and Calculator Inputs
The usual anion gap calculation uses sodium, potassium, chloride, and bicarbonate. Many providers apply the basic formula:
Anion gap = Sodium − (Chloride + Bicarbonate)Certain versions include potassium as well:
Anion gap = (Sodium + Potassium) − (Chloride + Bicarbonate)Both approaches approximate the relationship between measured cations and anions. The calculator input values usually come from routine serum electrolytes or a chemistry panel. Because each lab may report somewhat different units or reference intervals, the exact reference range should always be interpreted in context.
In practical use, the calculator requires accurate values for:
- Sodium, the principal measured cation Potassium, sometimes included in the formula Chloride, a primary measured anion Bicarbonate, often reported as CO2 on chemistry panels
These numbers reflect the patient’s current blood chemistry and help estimate whether there are additional unmeasured anions contributing to the result. A helpful way to think about the calculation is that it calculates the gap left behind by anions not listed directly on the panel.
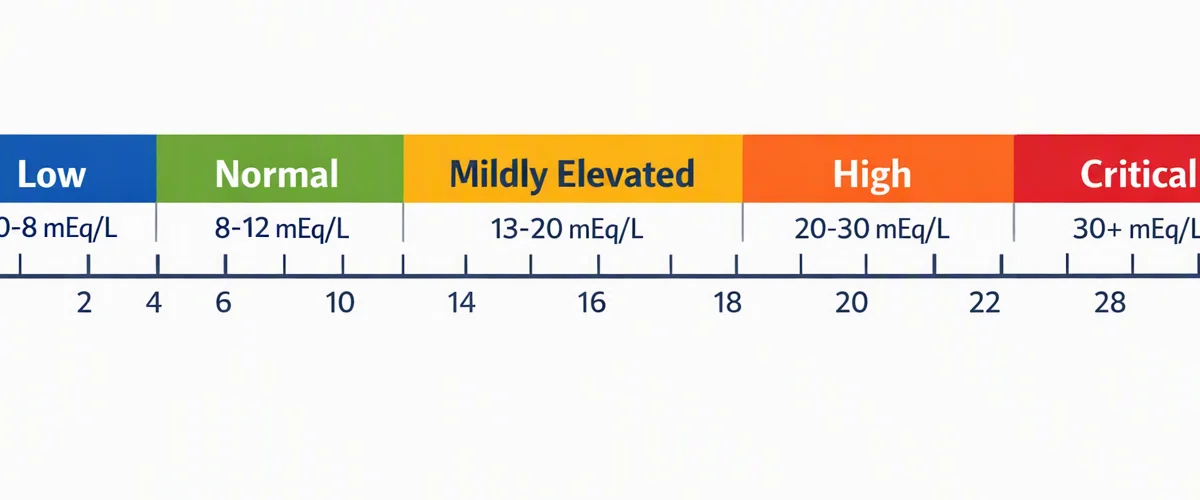
When used properly, the anion gap calculator provides a rapid diagnostic calculation that helps guide bedside decision-making. However, it should always be reviewed as part of the full clinical picture rather than treated as a standalone answer.
Typical Values and Corrected Anion Gap
A standard normal anion gap differs a bit by laboratory procedure and whether potassium is added. Many clinicians consider a value around 8 to 12 mEq/L normal when potassium is excluded, though the specific range should correspond to the lab’s reference range. A normal result does not always eliminate illness; it may simply indicate that the electrolyte pattern is balanced in a way that does not elevate the gap.
Albumin is a major unmeasured anion and has a significant effect on the anion gap. When albumin is low, the measured anion gap may seem falsely normal or low even if acids are present. This is why albumin correction is crucial so much in interpretation. In hypoalbuminemia, the corrected value can reveal hidden metabolic problems that the unadjusted number overlooks.
A corrected value estimates what the anion gap would be if albumin were normal. This is valuable because low albumin reduces the anion contribution from the protein fraction, creating an apparent anion deficit. Without adjustment, a patient with serious acid retention may seem less abnormal than they truly are.
Albumin correction is especially important in hospitalized patients, malnutrition, liver disease, or inflammation, where hypoalbuminemia is often seen. In these settings, the corrected value gives better clinical interpretation than the raw number alone. It can also help avoid missing a mixed acid-base disorder.
High Anion Gap vs Normal Anion Gap Disorders
Metabolic acidosis is the main category most often reviewed with the anion gap. The key distinction is whether the gap is increased or is still normal. A high anion gap acidosis implies that acids or acid equivalents have built up, increasing the amount of unmeasured anions in the blood.
Common causes of https://anion-gap-chart074.novacrestiq.com/posts/can-anemia-affect-anion-gap-a-introduction-to-test-interpretation high anion gap acidosis include lactic acidosis, ketoacidosis, and renal failure. In each case, the body is holding on to or producing acids faster than they can be removed or buffered. The anion gap rises because bicarbonate is consumed while accompanying anions remain present in circulation.
A normal anion gap acidosis, on the other hand, usually reflects bicarbonate loss with a corresponding rise in chloride. This is where the chloride shift becomes clinically relevant. The chloride increase helps preserve electroneutrality, but the tradeoff is a lower bicarbonate concentration and a persistent acidosis without a widened gap.
Identifying the difference matters because the causes and treatment strategies differ. High-gap disorders often prompt evaluation for toxic ingestion, tissue hypoxia, or severe metabolic crisis. Normal-gap disorders more often suggest gastrointestinal bicarbonate loss, renal tubular problems, or other patterns of chloride-related compensation.
Reading Results within Medical Context
The anion gap should be assessed together with the full presentation, rather than by itself. An arterial blood gas helps determine whether the patient has acidosis, alkosis, or a mixed acid-base picture. Meanwhile, serum electrolytes show whether alterations in chloride, bicarbonate, or sodium clarify the gap.
One useful concept is the delta gap, which compares the increase in anion gap to the fall in bicarbonate. It can help detect mixed acid-base problems. For example, if the gap is elevated above expected, there may be an additional metabolic alkalosis or chronic respiratory process. If the change is lower than expected, there may be a concurrent normal-gap acidosis.
Clinical reading becomes more useful when the anion gap is viewed as part of a broader acid-base analysis. A patient may have a high-gap metabolic picture on chemistry results, but the arterial blood gas may reveal compensation, overlap, or a second process. For this reason the anion gap calculator should assist, not replace, clinical reasoning.
When reviewing a serum bicarbonate result, it is also important to note whether the bicarbonate drop matches the chloride rise. If chloride is elevated while bicarbonate is low, the pattern may support a normal anion gap acidosis. If chloride is not elevated and bicarbonate is low, an accumulation of acids is more likely.
Common Causes of Abnormal Results
Irregular anion gap results often suggest a specific metabolic disturbance. A high gap may indicate lactic acidosis, ketoacidosis, renal failure, or contact with toxins. These conditions worsen acid load or reduce acid clearance, which increases anion concentration from unmeasured acids.
Lactic acidosis usually occurs when tissue oxygen delivery is impaired or when metabolism switches toward anaerobic pathways. Ketoacidosis may arise in diabetes, starvation, or alcohol-related states. Renal failure impairs the kidney’s ability to excrete acids and regenerate bicarbonate, resulting in a rising gap over time.
Normal-gap abnormalities are often linked to gastrointestinal loss of bicarbonate, such as diarrhea, or renal causes that lose bicarbonate. In these situations, chloride rises to replace the lost base, which keeps the anion gap from widening. That makes the chloride shift a important clue in separating acid loss from acid accumulation.
Some toxins can also produce unusual patterns or mixed disorders. Because toxin-related states may evolve quickly, a single calculator result should not be be used in isolation. Instead, it should be interpreted with the patient’s symptoms, medication exposures, renal function, and the full electrolyte panel.
Drawbacks of an Anion Gap Calculator
An anion gap calculator is helpful, but it has restrictions. One important issue is laboratory variation. Different analyzers and reporting methods can change the reference range, especially when potassium is counted or excluded. A result that seems abnormal in one scenario may be acceptable in another.
Testing error can also skew the result. Small inaccuracies in sodium, chloride, or bicarbonate may modify the gap enough to influence interpretation. This is particularly relevant when values are near the limit or when a patient has unusual clinical physiology, such as severe dehydration, marked protein abnormalities, or mixed acid-base states.
A further drawback is that the calculator does not identify the cause of the problem. It can suggest that the numbers indicate an acid-base issue, but it cannot identify whether the issue is lactic acid buildup, acidic ketosis, renal failure, toxic exposure, or bicarbonate loss. That requires medical history, physical exam, and additional testing.
Because of these factors, clinical judgment remains essential. The tool is most useful as a reference tool for clinical evaluation, rather than a replacement for thorough assessment. If the results do not match the patient’s condition, reconsider the inputs, confirm the sample, and review the broader context.
Frequently Asked Questions About Anion Gap and Chloride Shift
What is an anion gap calculator used for?
An anion gap calculator is utilized to estimate the discrepancy between observed cations and anions in serum chemistry. It assists check acid-base balance, identify possible metabolic acidosis, and support review of an acid-base disorder using values such as sodium, chloride, and bicarbonate.
How does chloride shift affect the anion gap?
The shift in chloride can help offset bicarbonate loss by increasing chloride levels, which may preserve the anion gap normal even when acidosis is present. That is why a pattern of higher chloride with decreasing bicarbonate often suggests a normal anion gap acidosis, while a gap rise without chloride replacement points to a high anion gap process.
What’s the normal anion gap range?
The normal anion gap depends on the lab and whether potassium is included in the formula. A lot of labs use a range around 8 to 12 mEq/L, but the exact reference range should consistently match the local method and reporting format.
How do albumin levels change the anion gap?
Albumin is a key unmeasured anion, so low albumin lowers the measured gap. In hypoalbuminemia, the raw result may fail to reflect the true acid load, which is why albumin correction is important for accurate interpretation.
When should a high anion gap be considered urgent?
A high gap may be urgent when it is associated with severe symptoms, rapid breathing, altered mental status, shock, or suspected lactic acidosis, ketoacidosis, renal failure, or toxins. In those settings, prompt evaluation with arterial blood gas, serum electrolytes, and full clinical assessment is necessary.